Updated 28/08/2026
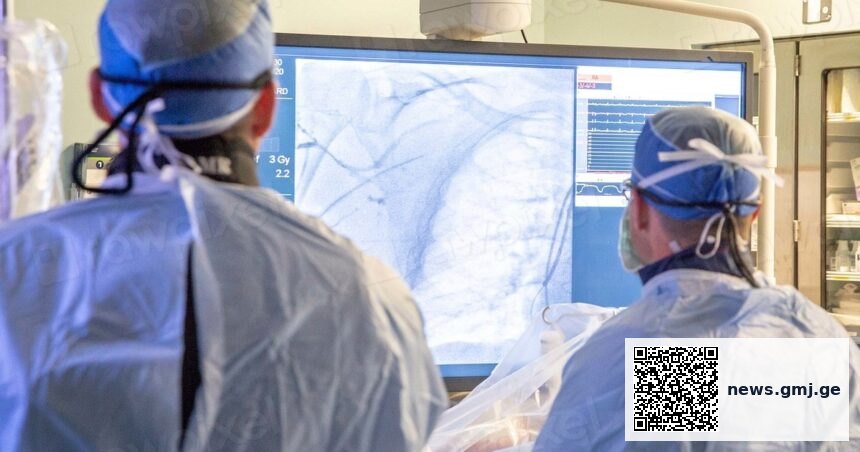
Photo: Cardiologists assigned to Naval Medical, by U.S. Navy Medicine · Public domain / CC0 · Source
Plain-language summary of research published in the Georgian Medical Journal. Written for the general public by the GMJ News editorial team.
An 87-year-old man arrived with a heart attack, three-vessel-level risk, and a body already carrying diabetes, hypertension, dyslipidaemia, and chronic kidney disease — the kind of profile that makes conventional open-heart bypass surgery dangerous. A case report in the Georgian Medical Journal documents how a staged, two-procedure hybrid strategy delivered complete revascularisation without a single complication.

A High-Risk Profile, By the Numbers
Risk stratification tools put the patient’s operative risk formally in the high-risk category: an STS score of 6.6% and a EuroSCORE II of 8.6% — scores clinicians use to estimate the probability of serious complications or death from major cardiac surgery. Coronary angiography confirmed critical two-vessel disease: a severe lesion in the left anterior descending artery involving the diagonal branch, plus significant narrowing in the mid-right coronary artery. Contemporary guidelines call for individualised, Heart Team-based decision-making in exactly this kind of case, rather than a single default procedure.
The Staged Hybrid Strategy
The multidisciplinary Heart Team chose hybrid coronary revascularisation (HCR) — combining minimally invasive surgical bypass with percutaneous coronary intervention (PCI) rather than a single full sternotomy operation. Stage one was a minimally invasive direct coronary artery bypass (MIDCAB): a left internal mammary artery graft to the LAD and its diagonal branch, performed via a left thoracotomy on a beating heart, avoiding a full sternotomy and cardiopulmonary bypass. Two days later, stage two followed: drug-eluting stent placement in the right coronary artery via PCI.

At a glance — the headline figures.
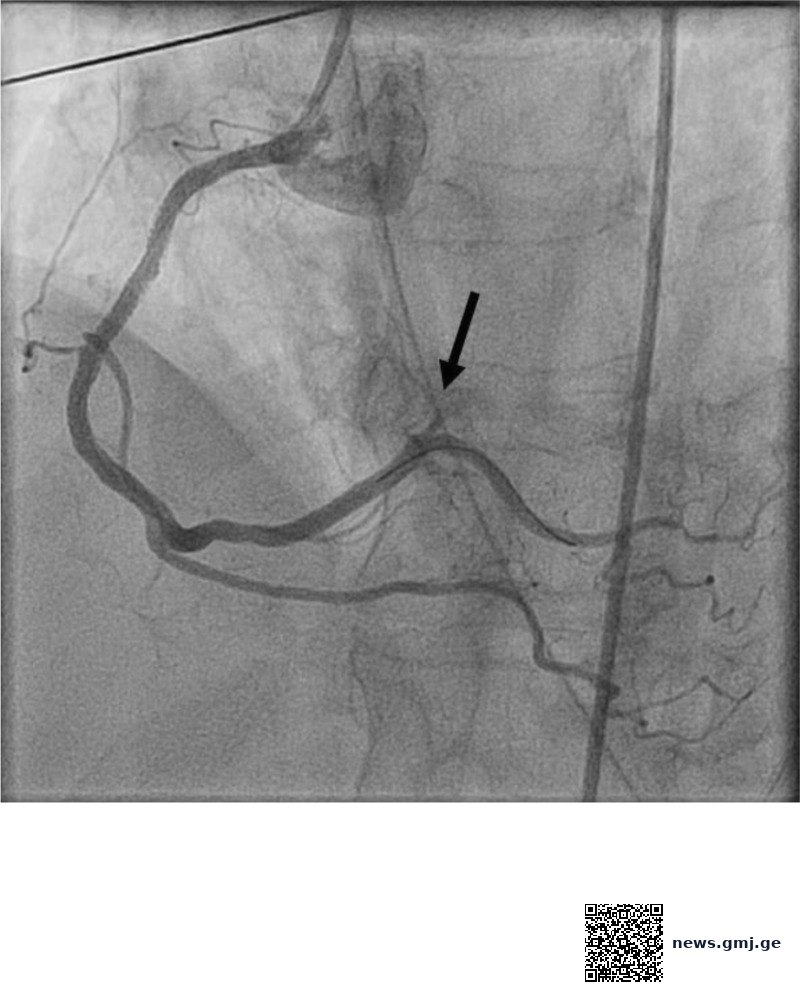
Coronary angiography showing the intervention on the right coronary artery (arrow), performed as the second stage of the hybrid strategy. Figure from the case report. Source: Georgian Medical Journal, Vol. 1 No. 1 (2026), DOI: 10.5281/zenodo.19132069.
Both procedures were completed without complications, and the patient was discharged on postoperative day five — a rapid recovery for an 87-year-old with this risk profile. The report credits the combination itself: the long-term durability of a LIMA-to-LAD graft, married to the lower physiological toll of a catheter-based procedure for the second vessel, rather than subjecting a frail patient to the full trauma of conventional bypass surgery for both lesions at once.
The broader point the authors draw out is about process as much as technique: a multidisciplinary Heart Team, evaluating this patient’s specific risk profile rather than defaulting to one standard revascularisation pathway, is what made a tailored two-stage strategy possible in the first place — and, the report argues, is increasingly what complete revascularisation in frail, elderly patients with acute coronary syndromes requires.
Read the Original Research
Original article: Heart Surgery at 80+: How a Staged Hybrid Approach Saved a High-Risk Patient
Published in: Georgian Medical Journal, Vol. 1 No. 1 (2026)
DOI: 10.5281/zenodo.19132069
📄 Read the full article at gmj.ge →
Georgian Medical Journal (GMJ) · ISSN 3088-4322 · gmj.ge · Open Access CC BY 4.0 · Published by the Public Health Institute of Georgia (PHIG). This summary is an independent editorial product of GMJ News; for clinical decisions, consult the original peer-reviewed article and a qualified professional.
Was this article helpful?
Disclaimer. This article is health journalism intended for general information and education. It is not medical advice and is not a substitute for professional diagnosis or treatment. Always consult a qualified healthcare provider about your individual circumstances. Full disclaimer →
Related Coverage



Editorial standards. This article was produced under the GMJ News editorial process, with oversight by the GMJ Editorial Board. Our editorial process. Spotted an error? Contact the editorial team.