


Home › Topics › The Mammography Debate
The Mammography Debate
GMJ News knowledge hub · last reviewed September 2026 · Georgian Medical Journal
SummaryStatisticsGlossaryGMJ newsFAQDocumentsOrganizationsResearch
Mammography is simultaneously one of the most evidence-backed and most honestly contested screening programmes in medicine: independent reviews credit it with meaningful breast cancer mortality reductions, and the same reviews concede that for every death prevented roughly three women are overdiagnosed and treated for cancers — especially DCIS — that would never have threatened them; meanwhile the US lowered its recommended starting age to 40 in 2024, density notification became universal, and AI reading matched radiologists in a large Swedish trial while nearly halving workload. Both halves of the ledger are set out below (see the WHO breast cancer fact sheet).
Key messages
THE BENEFIT CASE: real, trial-based, and older than ideal
Mammography's mortality evidence comes from randomised trials enrolling hundreds of thousands of women, mostly conducted decades ago: meta-analyses and the UK independent (Marmot) review settled on roughly a 20% relative reduction in breast cancer mortality among women invited to screen — for a 50-year-old attending for 20 years, in the order of one breast cancer death prevented per 200-250 women screened. Critics correctly note the trials predate modern adjuvant therapy, which shrinks screening's marginal contribution — when treatment rescues more of the late-diagnosed, early detection has less to add — and observational studies of modern programmes give a wide range of estimates. The defensible position: a real mortality benefit that is smaller in the treatment era than the campaign posters implied.
THE OVERDIAGNOSIS LEDGER: three for one
The same Marmot review that endorsed screening priced it honestly: for every breast cancer death prevented, roughly three women are overdiagnosed — treated with surgery, often radiotherapy and endocrine therapy, for cancers that would never have threatened them — about 19% of cancers diagnosed during the screening period. The engine is disproportionately DCIS, the pre-invasive lesion that mammography finds superbly and that now accounts for a fifth to a quarter of screen-detected disease despite most cases never progressing; trials of active monitoring for low-risk DCIS are underway precisely to stop paying the full treatment price for the indolent majority. Add the commoner nuisance harm — false positives, with cumulative recall risk approaching half of US women over a decade of annual screening — and the ledger has two heavy columns.
2024: THE US MOVES TO 40, AND DENSITY GOES UNIVERSAL
The USPSTF finalised a grade B recommendation for biennial screening from age 40 to 74 in 2024 — reversing its 2009 retreat to 50 — driven substantially by rising breast cancer incidence in women in their forties and persistently worse outcomes in Black women, whom the modelling suggested earlier screening would disproportionately benefit. In the same season, US federal rules made breast density notification universal: women must now be told when dense tissue both raises their risk and masks tumours on mammography. What the notification does not come with is a settled answer — supplemental ultrasound or MRI for dense breasts finds more cancer at the cost of more false positives, with no trial yet showing mortality benefit, leaving millions of women holding a risk letter and an open question.
THE AI TURN: the first genuine workload revolution
Screening mammography is radiologist-hungry — double reading in Europe consumes scarce specialist hours — and AI reading is the first technology to change that arithmetic in trials rather than press releases: in the Swedish MASAI randomised trial, AI-supported reading detected more cancers than standard double reading while cutting screen-reading workload by around 44%, without raising false positives. Similar results across European cohorts have moved AI from speculative to deployable, with national programmes now piloting it as one of two readers. The open questions are the field's own classics in new clothing: whether the extra cancers AI finds are the ones that matter or a fresh layer of overdiagnosis, and whether performance holds across vendors, populations and years — answerable only by the mortality follow-up now accumulating.
WHERE HONEST EXPERTS STILL DISAGREE
The mammography wars persist because the numbers support multiple readings: annual versus biennial intervals (biennial preserves most benefit at nearly half the false-positive cost — the USPSTF position — while some specialty societies advocate annual); starting age 40 versus 45-50 (absolute benefit is smallest and false positives highest in the youngest cohort); stopping age, where evidence virtually ends at 74; whether risk-stratified screening — intensity matched to individual risk, as trialled in WISDOM and European counterparts — should replace age-based rules entirely; and at the sceptical pole, long-standing arguments that in the modern treatment era total benefit no longer clearly exceeds total harm. No major body recommends abandoning screening; every serious body now publishes the harms alongside the benefits — itself the war's main victory.
PRACTICAL BOTTOM LINE
For average-risk women: screening from 40-50 to about 74, biennially or annually per local programme, carries a real mortality benefit alongside real chances of false alarm and overdiagnosis — attending is rational, informed attending more so, and the decision at 40-45 is legitimately closer than at 55. Know your density status and discuss what, if anything, to do with it. For higher-risk women — strong family history, BRCA variants, chest radiotherapy — different rules apply entirely: earlier starts, MRI-based protocols, specialist pathways. And if diagnosed with DCIS: ask what grade, what the progression risk actually is, and whether a monitoring trial or de-escalated treatment fits — the era of automatic maximal treatment for minimal lesions is ending.
Key statistics
~20%
relative reduction in breast cancer mortality among women invited to screening — the Marmot review's central estimate
Independent UK Panel, Lancet 2012~3 : 1
women overdiagnosed per breast cancer death prevented in the same review — the price tag published with the endorsement
Marmot review, 2012Age 40
the new USPSTF starting age for biennial screening (grade B, to 74), finalised in 2024 — reversing the 2009 move to 50
USPSTF final recommendation, April 2024~44%
screen-reading workload reduction with AI-supported reading in the Swedish MASAI randomised trial — with more cancers detected
Lang et al., Lancet Oncology 2023/2025~50%
cumulative probability of at least one false-positive recall over a decade of annual US screening
Breast Cancer Surveillance Consortium analysesSept 2024
US federal breast density notification became universal — every mammography report must disclose dense tissue and its implications
FDA MQSA rule, effective 2024Where the disagreement actually lies
Each claim scored by strength of evidence — not by popularity.
Mortality benefit in trial populations (strong)Strong · 80
Substantial overdiagnosis, DCIS-led (settled)Strong · 85
Benefit smaller in modern treatment era (likely)Contested · 65
AI reading matches double reading (strong, MASAI)Strong · 75
Supplemental imaging for density saves lives (unproven)Weak · 30
Screening does more harm than good overall (minority view)Weak · 25
Strong settledContested genuinely openWeak unsupported
Source: Editorial synthesis of trial meta-analyses, the Marmot review and modern programme data
Glossary of key terms
Latest GMJ coverage

AI-assisted mammography screening shows promise but requires careful interpretation of benefits
22/08/2026
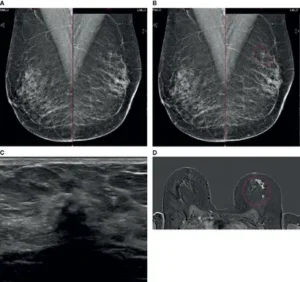
Late-life breast cancer screening reveals diagnosis in 79-year-old woman
11/08/2026

PROTEUS Trial Shows Promise for Perioperative Prostate Cancer Therapy
07/09/2026

Accelerated Biological Aging May Explain Rising Early-Onset Cancer in Younger Adults
07/09/2026
What makes prostate cancer aggressive? Biology, genetics, and clinical grading explained
14/08/2026

H. pylori screening yields fivefold return in gastric cancer prevention, health economics analysis shows
11/08/2026
Frequently asked questions 12 Q&A — structured for Google featured snippets and AI discovery
Knowledge hub: guidelines, conventions and reports
Organizations working in migration and health
Related health topics
Breast CancerOverdiagnosisPSA ScreeningMulti-Cancer Early DetectionWomen’s HealthCancer
About this hub. Produced by the GMJ News Editorial Team as a public-good service. Every statistic is linked to its primary source. Documents are preserved in the GMJ Repository with full attribution. Georgian Medical Journal · Contact the editorial team