Vitamin B12 deficiency can cause permanent nerve damage months or years before it triggers anaemia or abnormal blood counts, according to landmark clinical evidence. The mechanism operates through two independent biochemical pathways in myelin—the insulating sheath that wraps nerve fibres—both of which fail simultaneously when B12 levels drop. Understanding this timeline has urgent clinical implications: early detection and repletion can reverse neurological damage, but delayed diagnosis may result in irreversible demyelination.
Key takeaways
- B12 maintains myelin through two separate metabolic pathways; both fail at once when B12 drops
- 28% of patients with neurological B12 deficiency had completely normal blood counts at presentation, according to research published in The New England Journal of Medicine
- Early repletion can reverse nerve damage; late diagnosis may cause permanent demyelination
- Nerve injury precedes anaemia, making clinical vigilance essential even with normal haemoglobin
🟠 Moderate Evidence
B12 Deficiency: Two Metabolic Pathways, One Failure Point
How vitamin B12 maintains myelin integrity through parallel biochemical mechanisms
Conceptual model based on Scalabrino, Progress in Neurobiology, 2009 | Georgian Medical Journal News

The Two Pathways: How B12 Maintains Myelin
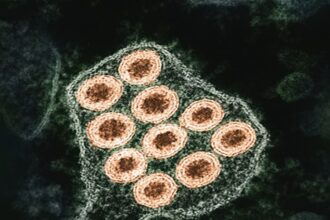
Myelin is a multilayered lipid sheath that insulates nerve axons and enables rapid electrical signal transmission. Without functional myelin, nerve conduction slows and neurological symptoms emerge. Vitamin B12 (cobalamin) maintains myelin through two independent but simultaneous biochemical mechanisms, both of which depend critically on adequate B12 levels.
The first pathway operates through methionine synthase. When B12 levels are adequate, the B12-dependent enzyme methylcobalamin converts homocysteine into methionine, which is then converted to S-adenosylmethionine (SAMe). SAMe donates the methyl groups required to synthesise phosphatidylcholine, one of myelin’s major structural lipid components. When B12 becomes deficient, methionine synthase activity collapses, SAMe production falls, and the synthesis of new myelin lipids stalls entirely.
The second pathway involves methylmalonyl-CoA mutase. B12 (in the form adenosylcobalamin) catalyses the conversion of methylmalonyl-CoA (MMA) to succinyl-CoA, clearing a toxic intermediate. When B12 is low, this enzyme cannot function. Methylmalonic acid accumulates, and abnormal fatty acids are incorporated directly into the myelin sheath itself, weakening its structural integrity from within. According to research by Giancarlo Scalabrino published in Progress in Neurobiology (2009), this dual-pathway failure explains why B12 deficiency causes such aggressive demyelination.
The Silent Window: Nerve Damage Before Anaemia Appears
A critical and often-missed clinical feature is that neurological damage from B12 deficiency can progress substantially before anaemia or macrocytosis appear on a complete blood count (CBC). In a landmark prospective study, Lindenbaum and colleagues at Columbia University reported in The New England Journal of Medicine (1988) that among patients presenting with neuropsychiatric symptoms caused by B12 deficiency, 28% had completely normal blood counts at the time of diagnosis. No anaemia. No macrocytosis. No red flag on routine screening.
This means the demyelination is progressing silently while the CBC remains reassuring. Patients may develop peripheral neuropathy, ataxia, cognitive dysfunction, or psychiatric symptoms without any haematological warning. The temporal dissociation between nerve damage onset and anaemia development creates a diagnostic window that, if missed, can close irreversibly.
28% of patients with neuropsychiatric symptoms from B12 deficiency had completely normal blood counts at presentation, with no anaemia or macrocytosis to raise clinical suspicion.
— Lindenbaum et al., Columbia University, New England Journal of Medicine, 1988
Reversibility vs. Permanence: The Critical Timing Window
The prognosis of B12-deficient neuropathy depends critically on the duration of deficiency before diagnosis and treatment. Scalabrino’s detailed mechanistic review (2009) demonstrates that early B12 repletion, if administered while demyelination is still in its acute phase, can halt the process and often reverse neurological symptoms. The myelin can regenerate if the insult is removed quickly enough.
However, if B12 deficiency persists unchecked for months or years, the demyelination becomes established and structural axonal loss occurs. At this stage, repletion may arrest further decline but cannot reverse the permanent neuronal damage already incurred. This explains the urgency of diagnosis: the longer the delay, the smaller the chance of full neurological recovery.
Clinicians should maintain high suspicion for B12 deficiency in patients presenting with peripheral neuropathy, ataxia, paresthesia, or cognitive/psychiatric decline, particularly in older adults, those on metformin or proton pump inhibitors, or patients with pernicious anaemia or malabsorption. A normal CBC should not reassure and should not delay B12 measurement if clinical suspicion is present. Early testing and repletion offer the best chance of preventing permanent neurological damage.
What this means
Frequently asked questions
Can B12 nerve damage be reversed if caught early?
Yes. If B12 deficiency is diagnosed and treated with repletion (oral, intramuscular, or sublingual forms) while demyelination is still acute—usually within weeks to months of symptom onset—neurological symptoms often improve and may fully resolve. However, if deficiency persists for years, axonal loss becomes permanent and recovery is incomplete, even with treatment. This is why early detection is critical.
Why does B12 deficiency cause neurological symptoms before anaemia?
Because myelin synthesis depends on B12 through the methionine synthase pathway, while red blood cell production depends on B12 through a different pathway (nucleotide synthesis). The nervous system is exquisitely sensitive to myelin damage, so neurological symptoms appear first. Anaemia develops later, as red blood cell turnover is slower than myelin breakdown.
Who is at highest risk for B12 deficiency?
Older adults, people taking metformin or proton pump inhibitors long-term, those with pernicious anaemia, inflammatory bowel disease, coeliac disease, or a history of gastric bypass surgery. Vegans and strict vegetarians without supplementation are also at risk, as B12 is found primarily in animal products.
As B12 deficiency remains a treatable cause of permanent neurological disability, the imperative is clinical vigilance and early detection. With modern assays, diagnosis is straightforward; the barrier is maintaining suspicion in primary care and specialist settings. Every patient with neuropathy, ataxia, or cognitive decline warrants B12 screening, irrespective of haemoglobin level. The window for reversibility is open—but only for those diagnosed in time. See the Clinical Updates section for more on vitamin deficiency screening guidelines and New Studies for recent evidence on B12 and neurological disease.
Source: Lindenbaum et al., New England Journal of Medicine, 1988 and Scalabrino, Progress in Neurobiology, 2009
Was this article helpful?
Disclaimer. This article is health journalism intended for general information and education. It is not medical advice and is not a substitute for professional diagnosis or treatment. Always consult a qualified healthcare provider about your individual circumstances. Full disclaimer →
Related Coverage



Editorial standards. This article was produced under the GMJ News editorial process, with oversight by the GMJ Editorial Board. Our editorial process. Spotted an error? Contact the editorial team.