🟠 Moderate Evidence
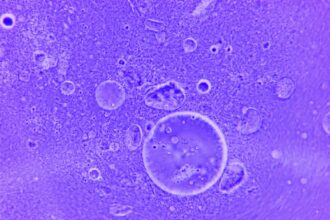
Mitochondria function as cellular decision-making centres that regulate inflammation, aging, and susceptibility to disease through energy signalling mechanisms, rather than merely serving as cellular power plants. A growing body of research demonstrates that mitochondrial dysfunction—not just energy depletion—underpins diverse pathologies from neurodegenerative disease to metabolic syndrome, suggesting that interventions targeting mitochondrial health may address multiple seemingly unrelated conditions.
Key takeaways
- Mitochondria act as signalling hubs that control cellular behaviour through energy management, not solely as ATP-production factories
- Damaged mitochondria release internal components that trigger immune activation and chronic low-grade inflammation independent of infection
- Age-related accumulation of dysfunctional mitochondria drives oxidative stress and systemic inflammation that characterises aging
- Neurodegenerative disease, cardiovascular disease, diabetes, autoimmune conditions, and cancer share a common molecular root in mitochondrial dysfunction across different tissues
Mitochondrial dysfunction as a shared mechanism across disease categories
Disease pathways linked to impaired mitochondrial function and energy signalling
Conceptual framework based on Signal Transduction and Targeted Therapy analysis | Georgian Medical Journal News

Energy signalling, not just energy production
Mitochondria traditionally characterised as cellular power plants that generate adenosine triphosphate (ATP) are increasingly understood as sophisticated signalling platforms. Research published in Signal Transduction and Targeted Therapy demonstrates that mitochondria regulate cellular decision-making through energy availability itself, functioning as metabolic switches that determine cell fate, proliferation, and death. Rather than ATP production being the sole function, the quantity, location, and timing of energy production determines whether cells maintain homoeostasis, mount immune responses, or undergo apoptosis.
This metabolic signalling extends beyond individual cells to coordinate tissue-level responses. Energy availability in specific cellular compartments—mitochondrial matrix, cristae, or intermembrane space—creates local chemical gradients that activate distinct signalling pathways, effectively allowing cells to integrate energy status with external stimuli and respond accordingly.
Mitochondrial damage as an inflammatory trigger independent of infection
When mitochondria sustain damage from oxidative stress, metabolic dysregulation, or genetic mutations, they release internal components including mitochondrial DNA (mtDNA) and cardiolipin into the cytoplasm. The innate immune system recognises these mitochondrial components as danger-associated molecular patterns (DAMPs), triggering activation of pattern recognition receptors and downstream inflammatory pathways such as the NLRP3 inflammasome. This mechanism explains how sterile inflammation—inflammation without infection—becomes established in chronic diseases.
This finding challenges the conventional view that inflammation requires pathogenic infection. According to research cited in Nature Immunology, the immune system continuously monitors mitochondrial integrity, and any failure to clear damaged organelles results in persistent immune activation. This provides a mechanistic link between mitochondrial dysfunction and the chronic systemic inflammation characteristic of aging and age-associated diseases.
Aging as a disorder of mitochondrial quality control
The accumulation of dysfunctional mitochondria represents a central feature of aging biology. As humans age, the cellular machinery responsible for removing damaged mitochondria—a process known as mitophagy—declines in efficiency. This failure allows mutant, energy-deficient mitochondria to persist and proliferate within cells, progressively impairing cellular energy metabolism and increasing oxidative stress. According to Cell Metabolism studies, the accumulation of dysfunctional mitochondria directly correlates with markers of cellular senescence and systemic inflammation in older adults.
This creates a cascade: impaired mitochondrial function reduces ATP production, triggering DAMP release and immune activation, which generates additional oxidative stress that further damages remaining functional mitochondria. The result is progressive decline in energy supply and escalating inflammation—the hallmark of aging at the cellular level. This mechanistic insight suggests that interventions enhancing mitochondrial quality control could slow multiple aging-related processes simultaneously.
A unified framework for seemingly diverse diseases
Neurodegenerative diseases including Parkinson’s disease and Alzheimer’s disease, cardiovascular disease, type 2 diabetes, obesity, autoimmune conditions, sepsis, and multiple cancer types traditionally classified as distinct pathologies share a common thread: failure of mitochondrial energy metabolism and quality control. Neurons, cardiomyocytes, and pancreatic β-cells are among the most metabolically demanding tissues, and their particular vulnerability to mitochondrial dysfunction explains their prominence in age-related disease.
This unifying framework, detailed in Signal Transduction and Targeted Therapy, suggests that the apparent diversity of modern diseases may reflect the same underlying pathophysiology—mitochondrial insufficiency—expressing itself through different organ-specific mechanisms. A 65-year-old patient with cognitive decline, hypertension, and glucose dysregulation may have three seemingly separate diagnoses, but each reflects progressive failure of mitochondrial function in brain, vasculature, and pancreas respectively.
Mitochondrial dysfunction is not an incidental finding in aging and disease, but a primary driver that explains the convergence of inflammation, energy deficiency, and cellular senescence across diverse organ systems.
Limitations of antioxidant-only approaches
Conventional antioxidant therapies target oxidative damage itself, attempting to neutralise free radicals through supplementation with compounds such as vitamin C, vitamin E, or polyphenols. However, this approach addresses a symptom—oxidative stress—rather than the root cause: the failure of cells to remove damaged mitochondria and maintain energy homeostasis. According to research in Nature Reviews Molecular Cell Biology, antioxidant supplementation has shown limited efficacy in clinical trials for major diseases precisely because it does not restore mitochondrial function or enhance mitophagy.
The spatial and temporal context of oxidative damage matters more than its absolute magnitude. Oxidative stress occurring in mitochondria damaged beyond repair represents a signal for quality control removal. Scavenging that signal with antioxidants may actually impair the cell’s ability to clear dysfunctional organelles, potentially worsening outcomes. A more effective strategy targets the underlying defect: restoring mitochondrial biogenesis, enhancing mitophagy, and improving energy signalling capacity.
What this means
Frequently asked questions
Can mitochondrial function be measured in clinical practice?
Several biomarkers reflecting mitochondrial status are available. Serum lactate elevation indicates impaired mitochondrial ATP production. Mitochondrial DNA copy number in blood or muscle tissue quantifies mitochondrial quantity. Muscle biopsy and electron microscopy remain gold standards but are invasive. Non-invasive functional assessments including cardiopulmonary exercise testing and assessment of mitochondrial ATP synthesis via phosphorus-31 magnetic resonance spectroscopy are research-grade tools being translated to clinical settings.
Which interventions have evidence for enhancing mitochondrial function?
Structured aerobic and resistance exercise consistently improves mitochondrial biogenesis and function in humans across age groups, with effects visible within weeks. Caloric restriction and intermittent fasting activate SIRT1 and AMPK pathways that enhance mitophagy and mitochondrial renewal. Pharmacological activators of these pathways including NAD+ precursors (nicotinamide riboside, NMN) show promise in animal models and early human studies, though large randomised controlled trials in clinical populations are ongoing. Nutritional factors including polyphenols from whole foods may support mitochondrial function, though isolated supplement efficacy remains contested.
If mitochondrial dysfunction underlies multiple diseases, why haven’t mitochondria-targeting drugs succeeded clinically?
Early mitochondrial medicine focused on antioxidants and free radical scavengers without addressing the fundamental problem: removal of damaged mitochondria and restoration of biogenesis. Additionally, many drugs fail to achieve sufficient mitochondrial concentrations or affect off-target pathways. Newer-generation agents targeting specific aspects of mitochondrial biology—such as enhancers of mitophagy (e.g., urolithin A) or activators of mitochondrial biogenesis (PGC-1α activators)—are in clinical development with more optimistic early data, though long-term efficacy and safety require sustained investigation.
The reconceptualisation of mitochondria from passive batteries to active decision-making centres offers a biological framework for understanding why multiple seemingly disparate diseases become more common with aging and why they often cluster within individuals. This perspective suggests that precision medicine’s future may lie not in targeting individual diseases but in restoring the fundamental cellular machinery—mitochondrial health—that underpins multiple systems simultaneously. Ongoing clinical trials in cardiovascular, metabolic, and neurological disease will test whether interventions optimising mitochondrial function deliver the coordinated clinical improvements that this biology predicts.
Source: Signal Transduction and Targeted Therapy (2025); DOI:10.1038/s41392-025-02253-4
Was this article helpful?
Disclaimer. This article is health journalism intended for general information and education. It is not medical advice and is not a substitute for professional diagnosis or treatment. Always consult a qualified healthcare provider about your individual circumstances. Full disclaimer →
Related Coverage



Editorial standards. This article was produced under the GMJ News editorial process, with oversight by the GMJ Editorial Board. Our editorial process. Spotted an error? Contact the editorial team.