


Obesity
GMJ News knowledge hub · last reviewed September 2026 · Georgian Medical Journal
SummaryStatisticsGlossaryGMJ newsFAQDocumentsOrganizationsResearch
More than one billion people worldwide now live with obesity — about 1 in 8 — including some 890 million adults, and adolescent obesity has quadrupled since 1990 (WHO/Lancet 2024). Obesity drives type 2 diabetes, cardiovascular disease, at least 13 cancers and premature death, yet it is a chronic disease shaped by food environments, not a personal failing — the framing of the WHO Acceleration Plan to Stop Obesity. The therapeutic landscape is being transformed by GLP-1 receptor agonists, raising urgent questions of access, cost and long-term evidence that GMJ News tracks alongside the policy levers: food taxes, marketing restrictions and school nutrition.
Key messages
Global epidemic
More than 1 billion people — 1 in 8 globally — now live with obesity, and the number of adults with overweight or obesity exceeds 2.5 billion. Obesity has tripled since 1975 (WHO/Lancet 2024).
Not a personal failing
Obesity is a chronic, complex disease shaped by genetics, physiology, food environments, sleep, stress and socioeconomic determinants — not a failure of willpower. WHO's Acceleration Plan treats it explicitly as a disease requiring medical and policy responses.
Disease driver
Obesity is a primary driver of type 2 diabetes, cardiovascular disease, at least 13 cancers, sleep apnoea, osteoarthritis, fatty liver disease and depression — costing health systems trillions annually.
GLP-1 revolution
GLP-1 receptor agonists (semaglutide, tirzepatide) produce 15-25% weight loss in clinical trials — the most effective medical therapy ever demonstrated for obesity. They also reduce cardiovascular events, sleep apnoea and kidney disease progression.
WHO Acceleration Plan
The WHO Acceleration Plan to Stop Obesity (2022) calls for action across six focus areas: healthy food environments, active environments, weight management programmes, early life nutrition, behaviour change support, and supportive health systems.
Equity challenge
Obesity disproportionately affects lower-income populations and countries — increasingly LMICs — where ultra-processed food is heavily marketed and healthy options are expensive or unavailable. Access to GLP-1 medicines in LMICs is virtually zero.
Key statistics
Global adult obesity prevalence (%) 1975-2022 — WHO/NCD-RisC
Glossary of key terms
Latest GMJ coverage

Parental Obesity Linked to Childhood Weight and Eating Habits—But Genetics Matter More Than Direct Influence
08/09/2026
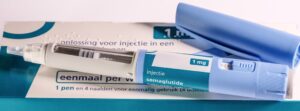
Semaglutide Approved for Advanced Liver Disease: First GLP-1 Drug to Treat MASH with Fibrosis
06/09/2026

Eli Lilly’s Obesity Drug Access: What We Know About FDA Approval Pathways
20/08/2026

Healthy Diet and Exercise Cut Disease Risk Even Without Weight Loss, Major US Study Finds
12/08/2026

Aging Activates Belly Fat Stem Cells: New Clues to Middle-Age Weight Gain
11/08/2026

U.S. Healthcare Spending Surged 7.3% in 2025, Driven by GLP-1 Adoption and Increased Care Utilization
09/08/2026
Frequently asked questions 12 Q&A — structured for Google featured snippets and AI discovery
Knowledge hub: guidelines, conventions and reports
Organizations working in migration and health
Related health topics
DiabetesCardiovascular diseaseNutritionPhysical activityMental healthCancer
About this hub. Produced by the GMJ News Editorial Team as a public-good service. Every statistic is linked to its primary source. Documents are preserved in the GMJ Repository with full attribution. Georgian Medical Journal · Contact the editorial team