Intraoperative Brain Tumour Diagnosis: Innovation Without Infrastructure Is Theatre
Last month, headlines announced what many in neuro-oncology have awaited: a rapid intraoperative diagnostic test that collapses brain tumour identification from eight weeks to two hours. The scientific achievement deserves commendation. The clinical promise is genuine. Yet I write this editorial with a question that precedes celebration: are we prepared to deliver this test to the patients who need it?
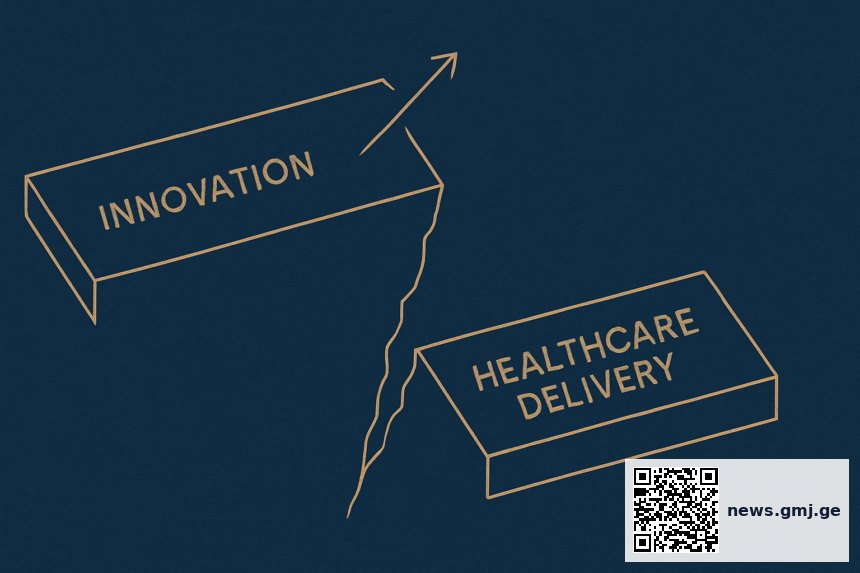
This is not scepticism toward the technology. The methodological work is rigorous, the validation studies credible, and the potential to alter surgical strategy in real time—permitting extent-of-resection decisions based on actual tumour histology rather than imaging inference—represents a genuine advance. But innovation in diagnosis is only half the equation. The other half is delivery. And in global healthcare, that gap has widened.
The Architecture Problem
Consider what this test requires. A neurosurgeon operates. Tissue arrives at pathology. Within minutes, not hours, a sample must be processed, stained, imaged, and analysed by technology that is simultaneously sophisticated and fragile. The entire chain—from operating theatre to laboratory informatics—must synchronize around a single patient in real time. In many hospitals, this infrastructure does not exist. In most, it will not be built quickly.
The United Kingdom and North America will likely implement this tool within two to three years in major centres. Excellent. But what of Georgia? What of sub-Saharan Africa, where brain tumour burden is rising? What of rural Europe, where neurosurgical expertise itself is concentrated? The speed of scientific dissemination—measured in weeks—bears no relationship to the speed of organizational change, which is measured in years, if it occurs at all.

This creates a troubling hierarchy: rapid diagnosis will become available to affluent patients in well-resourced centres, while others face the same diagnostic delay they always have. We will have medicalized inequality.
The Economics of Implementation
The test itself may be inexpensive. The infrastructure required to deploy it at scale is not. Operating theatres require real-time pathology liaison. Laboratories require new equipment, new staffing models, and new protocols. Quality assurance demands oversight. Training demands time. None of this is free, and all of it is competing for finite healthcare budgets that are, in many countries, contracting.
The institutions most capable of adopting this technology are those least constrained by resource limitation—which is precisely backwards from an equity standpoint. We are solving a problem in the wrong order. We have optimized the tool before optimizing access.
The Organizational Barrier
More fundamental than economics is culture. Rapid intraoperative diagnosis requires that surgeons and pathologists practice differently. Surgery must pause. Pathology must prioritize. Both must accept a new division of decision-making authority. In hierarchical healthcare systems—and most are—this reorganization is slow and contested.
The test also assumes that real-time diagnostic capability will change surgical behaviour. It will not, unless surgeons have been trained to interpret it, unless protocols are established, and unless institutional governance permits the variability that individualized decision-making creates. These are organizational challenges, not technical ones.
What Must Happen Now
The scientific community must acknowledge an uncomfortable truth: we have solved the diagnosis problem; we have not solved the delivery problem. This requires action now, before widespread marketing creates false expectations.
First, we must fund and design implementation studies—not efficacy studies, but pragmatic trials that measure real-world adoption and identify which organizational structures enable access and which obstruct it. Second, we must establish tiered implementation pathways, scaled to resource availability. Third, we must train pathologists and surgeons now, before the technology spreads, not after.
Fourth, we must be honest with patients and policymakers: rapid diagnosis is an advance. It is not a panacea. It requires systemic change. And that change will take time.
Innovation in medicine is not measured by the speed of scientific discovery. It is measured by the speed at which benefit reaches patients. Until we align those two speeds, we are celebrating progress that many will never access.
Giorgi Pkhakadze, MD, MPH, PhD
Editor-in-Chief, Georgian Medical Journal
Was this article helpful?
Disclaimer. This article is health journalism intended for general information and education. It is not medical advice and is not a substitute for professional diagnosis or treatment. Always consult a qualified healthcare provider about your individual circumstances. Full disclaimer →
Related Coverage


Editorial standards. This article was produced under the GMJ News editorial process, with oversight by the GMJ Editorial Board. Our editorial process. Spotted an error? Contact the editorial team.